Search Previous Year Questions

Find real questions from previous competitive exam papers with answers and solutions.

Leave the keyword blank to browse saved questions for your selected exam, newest papers first. Add a keyword, year or topic to narrow the results.

Browse complete papers
Showing 10 question(s)
Clear

Question 11

AIIMS Nursing Officer 2025• Section 1

During childbirth, after the baby’s head is delivered, it pulls back toward the perineum like a “turtle sign," suggesting shoulder dystocia. What should be the first maneuver used to manage this emergency?

  1. AOption (a)

    McRoberts maneuver

  2. BOption (b)

    Woods’ screw maneuver

  3. COption (c)

    Applying fundal pressure

  4. DOption (d)

    Zavanelli maneuver

View answer & explanation

Correct answer

Answer: (a)A.

McRoberts maneuver

Why this answer is correct

Correct Answer: McRoberts maneuver

Rationale:

  • The “turtle sign” occurs when the baby’s head retracts back toward the perineum immediately after birth of the head, indicating shoulder dystocia, an obstetric emergency where the anterior shoulder becomes trapped behind the maternal pubic bone.
  • The McRoberts maneuver is the recommended first-line intervention because it is simple, safe, and effective. It works by sharply flexing the mother's thighs onto her abdomen, which widens the pelvic outlet and straightens the sacrum, allowing the baby’s shoulder to slip beneath the pubic symphysis.
  • This maneuver resolves more than 40–50% of shoulder dystocia cases without the need for additional, more invasive procedures.
  • Early and correct use of the McRoberts maneuver reduces maternal and fetal complications such as brachial plexus injury, hypoxia, or postpartum hemorrhage.
  • Therefore, upon recognizing the turtle sign, the McRoberts maneuver must be initiated immediately to relieve shoulder impaction safely.

Explanation of Other Options:

Woods’ screw maneuver

  • Rationale: This is an internal rotational maneuver used only if McRoberts and suprapubic pressure fail. It rotates the fetal shoulders but is not the first step.

Applying fundal pressure

  • Rationale: Fundal pressure is contraindicated in shoulder dystocia because it can worsen impaction and cause severe fetal injury.

Zavanelli maneuver

  • Rationale: This involves pushing the fetal head back into the vagina for emergency cesarean section. It is a last-resort, high-risk intervention when all other attempts fail.

Conclusion:

  • The presence of a “turtle sign” signals shoulder dystocia. The safest and most effective initial action is the McRoberts maneuver, making it the first step in managing this obstetric emergency.
Question 12

AIIMS Nursing Officer 2025• Section 1

A patient taking lithium for a long time reports nausea, vomiting, and a coarse hand tremor. What should the nurse advise?

  1. AOption (a)

    Skip the next lithium dose and come to the clinic right away for a lithium level test

  2. BOption (b)

    Increase water intake and lower salt intake

  3. COption (c)

    Take the next lithium dose with food and plenty of water

  4. DOption (d)

    These symptoms are normal and will go away soon

View answer & explanation

Correct answer

Answer: (a)A.

Skip the next lithium dose and come to the clinic right away for a lithium level test

Why this answer is correct

Correct Answer: Skip the next lithium dose and come to the clinic right away for a lithium level test

Rationale:

  • Lithium has a very narrow therapeutic range, and even slight increases in serum levels can cause toxicity. Symptoms such as nausea, vomiting, diarrhea, coarse hand tremor, weakness, and confusion are classic signs of lithium toxicity.
  • A coarse tremor is a key indicator of toxicity and is more serious than the fine tremor seen in stable lithium therapy, making immediate evaluation necessary.
  • Continuing the lithium dose may worsen toxicity and lead to severe complications such as seizures, arrhythmias, kidney failure, or coma. Therefore, the patient should be advised to hold (skip) the next dose.
  • Prompt testing of the serum lithium level is the safest and most appropriate step to confirm toxicity and guide urgent medical treatment, including hydration or potential hospitalization.
  • Therefore, the correct advice is to stop the next dose and visit the clinic immediately for a lithium level check.

Explanation of Other Options:

Increase water intake and lower salt intake

  • Rationale: Reducing salt intake actually increases lithium levels, making toxicity worse. Hydration is helpful but does not replace the need for urgent evaluation.

Take the next lithium dose with food and plenty of water

  • Rationale: Continuing lithium during toxicity can lead to life-threatening complications. Taking it with food only reduces stomach upset, not toxicity.

These symptoms are normal and will go away soon

  • Rationale: These symptoms are not normal but strongly suggest toxicity. Reassurance without action is unsafe and dangerous.

Conclusion:

  • Symptoms such as nausea, vomiting, and a coarse tremor indicate possible lithium toxicity. The safest and most appropriate action is to hold the next dose and seek immediate evaluation for a lithium level test to prevent serious complications.

Question 13

AIIMS Nursing Officer 2025• Section 1

A patient with panic disorder is taught how to notice negative thoughts, question them, and use relaxation techniques when anxiety rises. This type of therapy, which aims to change unhelpful thinking and behavior, is called:

  1. AOption (a)

    Cognitive Behavioral Therapy (CBT)

  2. BOption (b)

    Interpersonal Therapy

  3. COption (c)

    Group Therapy

  4. DOption (d)

    Psychoanalytic Therapy

View answer & explanation

Correct answer

Answer: (a)A.

Cognitive Behavioral Therapy (CBT)

Why this answer is correct

Correct Answer: Cognitive Behavioral Therapy (CBT)

Rationale:

  • The scenario describes a structured approach where the patient learns to identify negative thoughts, challenge irrational beliefs, and apply relaxation or coping techniques during anxiety episodes. This method is characteristic of Cognitive Behavioral Therapy (CBT).
  • CBT focuses on the connection between thoughts, feelings, and behaviors, helping patients replace distorted thinking patterns with more realistic and constructive thoughts.
  • For panic disorder, CBT is considered a first-line, evidence-based treatment because it reduces fear responses, improves emotional regulation, and teaches long-term coping strategies.
  • Techniques used in CBT—such as cognitive restructuring, relaxation training, exposure therapy, and breathing control—are specifically effective in reducing panic attacks and anticipatory anxiety.
  • Therefore, the therapy described—changing unhelpful thoughts and behaviors while practicing relaxation—best matches Cognitive Behavioral Therapy.

Explanation of Other Options:

Interpersonal Therapy

  • Rationale: Interpersonal Therapy (IPT) focuses on relationships, communication conflicts, grief, and social roles. It does not specifically target panic symptoms or cognitive distortions.

Group Therapy

  • Rationale: Group Therapy involves sharing experiences in a therapeutic group. While useful, it does not focus on systematically correcting negative thought patterns.

Psychoanalytic Therapy

  • Rationale: Psychoanalytic therapy explores unconscious conflicts, early childhood experiences, and repressed emotions. It is not the primary method for treating panic disorder and does not teach structured coping skills.

Conclusion:

  • Teaching a patient to challenge negative thoughts, modify behavior, and practice relaxation aligns with the principles of Cognitive Behavioral Therapy (CBT), making it the most appropriate answer.

Question 14

AIIMS Nursing Officer 2025• Section 1

A 3-month-old baby has a reducible umbilical hernia. Which observation should be reported to the doctor immediately?

  1. AOption (a)

    The hernia becomes firm, changes color, and the baby suddenly starts vomiting

  2. BOption (b)

    The hernia looks normal in color and the skin feels warm

  3. COption (c)

    The bulge becomes more noticeable when the baby cries

  4. DOption (d)

    The hernia is soft and can be gently pushed back into the abdomen

View answer & explanation

Correct answer

Answer: (a)A.

The hernia becomes firm, changes color, and the baby suddenly starts vomiting

Why this answer is correct

Correct Answer: The hernia becomes firm, changes color, and the baby suddenly starts vomiting

Rationale:

  • A reducible umbilical hernia is generally harmless in infants, but it can become dangerous if it progresses to incarceration or strangulation. This occurs when a portion of the intestine becomes trapped, cutting off blood supply.
  • Signs such as the hernia becoming firm, discolored (red, purple, or dark), tender, or non-reducible are classic warnings of strangulation.
  • Sudden onset of vomiting, irritability, or crying indicates possible bowel obstruction or compromised blood flow, which is a medical emergency.
  • If strangulation occurs, the infant can develop severe complications including necrosis of the bowel, sepsis, and shock. Immediate medical intervention is required.
  • Therefore, a change in firmness, color, and vomiting must be reported to the doctor immediately as it indicates a surgical emergency.

Explanation of Other Options:

The hernia looks normal in color and the skin feels warm

  • Rationale: Warm skin is normal in infants, and a healthy umbilical hernia typically appears normal in color. This does not suggest danger.

The bulge becomes more noticeable when the baby cries

  • Rationale: Crying increases abdominal pressure, making the hernia more visible. This is a normal finding in reducible hernias.

The hernia is soft and can be gently pushed back into the abdomen

  • Rationale: A soft, reducible hernia is considered normal and safe. No emergency intervention is needed.

Conclusion:

  • A reducible umbilical hernia becomes an emergency when it turns firm, discolored, painful, or is associated with vomiting. These signs indicate possible strangulation and must be reported immediately.

Question 15

AIIMS Nursing Officer 2025• Section 1

In which city is the main office of UNESCO (United Nations Educational, Scientific and Cultural Organization) located?

  1. AOption (a)

    Paris, France

  2. BOption (b)

    New York, USA

  3. COption (c)

    Vienna, Austria

  4. DOption (d)

    Geneva, Switzerland

View answer & explanation

Correct answer

Answer: (a)A.

Paris, France

Why this answer is correct

Correct Answer: Paris, France

Rationale:

  • The United Nations Educational, Scientific and Cultural Organization (UNESCO) is a specialized agency of the United Nations that focuses on education, culture, science, and communication to promote global peace and cooperation.
  • The headquarters of UNESCO is located in Paris, France, where the organization was established in 1945 after World War II to build peace through cultural understanding and education.
  • UNESCO’s main office in Paris hosts major global programs, executive meetings, research initiatives, and coordination of worldwide activities such as World Heritage Sites, literacy missions, and scientific collaboration.
  • Its location in Paris symbolizes the city’s long-standing tradition of supporting international cooperation, arts, culture, and diplomacy.
  • Therefore, based on historical and organizational facts, the headquarters of UNESCO is in Paris, France.

Explanation of Other Options:

New York, USA

  • Rationale: New York is the headquarters of the United Nations (UN), not UNESCO.

Vienna, Austria

  • Rationale: Vienna hosts UN agencies such as the IAEA (International Atomic Energy Agency) and UNODC, but not UNESCO.

Geneva, Switzerland

  • Rationale: Geneva is home to WHO, UNHCR, and other UN bodies, but not UNESCO headquarters.

Conclusion:

  • The main office of UNESCO is located in Paris, France, making it the correct answer based on United Nations organizational structure.

Question 16

AIIMS Nursing Officer 2025• Section 1

A woman in labor has a cervical dilation of 5 cm, 80% effacement, and strong contractions coming every 3–4 minutes. Which phase of the first stage of labor is she in?

  1. AOption (a)

    Active phase

  2. BOption (b)

    Latent phase

  3. COption (c)

    Transition phase

  4. DOption (d)

    Second stage

View answer & explanation

Correct answer

Answer: (a)A.

Active phase

Why this answer is correct

Correct Answer: Active phase

Rationale:

  • The first stage of labor is divided into three phases: latent, active, and transition. These phases are distinguished by the degree of cervical dilation, the strength of contractions, and the mother’s labor progress.
  • A cervical dilation of 5 cm with 80% effacement and strong, regular contractions every 3–4 minutes clearly falls within the active phase of labor.
  • The active phase typically spans from 4 cm to 7 cm dilation, characterized by more rapid cervical change and stronger, closer contractions that facilitate fetal descent.
  • Women in the active phase require close monitoring of contractions, fetal heart rate, pain management, and preparation for the upcoming transition phase.
  • Therefore, based on cervical dilation and contraction pattern, the woman is in the active phase of the first stage of labor.

Explanation of Other Options:

Latent phase

  • Rationale: The latent phase usually includes slow cervical dilation from 0 to 3–4 cm. Contractions are mild to moderate and occur less frequently compared to this scenario.

Transition phase

  • Rationale: The transition phase occurs at 8–10 cm dilation and is the most intense phase. Since the patient is only 5 cm dilated, this phase does not apply.

Second stage

  • Rationale: The second stage begins at full dilation (10 cm) and ends with birth. The patient is not yet fully dilated.

Conclusion:

  • With 5 cm dilation, 80% effacement, and strong contractions every 3–4 minutes, the woman is correctly identified as being in the active phase of the first

Question 17

AIIMS Nursing Officer 2025• Section 1

The Burns–Marshall maneuver is used in obstetrics during which specific situation?

  1. AOption (a)

    To help deliver the after-coming head in a breech birth

  2. BOption (b)

    To assist with removal of the placenta

  3. COption (c)

    To control postpartum bleeding

  4. DOption (d)

    To correct shoulder dystocia

View answer & explanation

Correct answer

Answer: (a)A.

To help deliver the after-coming head in a breech birth

Why this answer is correct

Correct Answer: To help deliver the after-coming head in a breech birth

Rationale:

  • The Burns–Marshall maneuver is a well-known obstetric technique specifically used during a breech delivery to assist in delivering the after-coming head.
  • In this maneuver, after the baby’s body has been delivered in a breech birth, the infant is allowed to hang momentarily to provide gentle downward traction by gravity. This helps flex the fetal head naturally.
  • Once the head begins to appear at the perineum, the practitioner applies controlled upward traction to complete delivery. This helps prevent complications such as entrapment of the after-coming head, which is a major risk in breech births.
  • The goal of the Burns–Marshall maneuver is to maintain correct alignment of the fetal head, minimize trauma, and ensure a safe vaginal breech delivery.
  • Therefore, this maneuver is used specifically for assisting the delivery of the after-coming head during a breech presentation.

Explanation of Other Options:

To assist with removal of the placenta

  • Rationale: Placental delivery involves controlled cord traction (Brandt–Andrews maneuver), not the Burns–Marshall maneuver.

To control postpartum bleeding

  • Rationale: Management of postpartum hemorrhage includes uterotonics, uterine massage, and surgical interventions—not this maneuver.

To correct shoulder dystocia

  • Rationale: Shoulder dystocia is managed with maneuvers like McRoberts, suprapubic pressure, or Woods’ screw maneuver, not Burns–Marshall.

Conclusion:

  • The Burns–Marshall maneuver is exclusively used to assist delivery of the after-coming head in a breech birth, making it the correct choice.

Question 18

AIIMS Nursing Officer 2025• Section 1

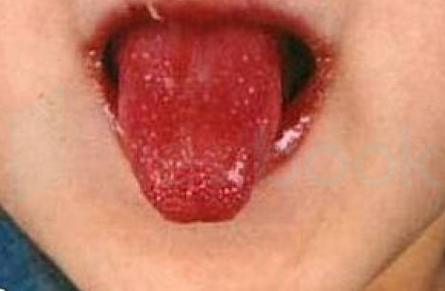
A toddler has had a high fever for 5 days, red eyes without discharge, a “strawberry” tongue, a widespread rash, and redness/swelling of the hands and feet. These signs point to which condition?

  1. AOption (a)

    Kawasaki disease

  2. BOption (b)

    Measles (rubeola)

  3. COption (c)

    Scarlet fever

  4. DOption (d)

    Hand, foot, and mouth disease

View answer & explanation

Correct answer

Answer: (a)A.

Kawasaki disease

Why this answer is correct

Correct Answer: Kawasaki disease

Rationale:

  • The symptoms described—high fever for 5 days, red eyes without discharge, strawberry tongue, widespread rash, and red/swollen hands and feet—strongly indicate Kawasaki disease, a type of acute systemic vasculitis that primarily affects children under 5 years of age.
  • Kawasaki disease typically presents with prolonged fever (≥5 days) along with at least four of the following: bilateral non-purulent conjunctivitis, oral changes such as strawberry tongue or cracked lips, polymorphous rash, extremity changes like swelling or redness, and cervical lymphadenopathy.
  • The red, swollen extremities and strawberry tongue are highly characteristic features, and the absence of eye discharge suggests inflammatory—not infectious—conjunctivitis, further supporting Kawasaki disease.
  • Kawasaki disease is clinically important because untreated cases can lead to serious complications such as coronary artery aneurysms. Early recognition and treatment with IVIG and aspirin greatly reduce cardiovascular risks.
  • Therefore, the combination of prolonged fever plus mucocutaneous and extremity changes points clearly to Kawasaki disease.

Explanation of Other Options:

Measles (rubeola)

  • Rationale: Measles causes cough, coryza, conjunctivitis with discharge, Koplik spots, and a descending rash. Swollen hands/feet and strawberry tongue are not typical findings.

Scarlet fever

  • Rationale: Scarlet fever features strawberry tongue and a sandpaper-like rash, but it does not cause red, swollen hands/feet or conjunctivitis without discharge.

Hand, foot, and mouth disease

  • Rationale: HFMD causes painful ulcers and vesicles on hands, feet, and mouth—not strawberry tongue, prolonged fever, or conjunctivitis.

Conclusion:

  • The classic constellation of fever, strawberry tongue, non-purulent conjunctivitis, rash, and extremity swelling is diagnostic of Kawasaki disease, making it the correct answer.

Question 19

AIIMS Nursing Officer 2025• Section 1

A 34-week pregnant woman has an NST showing a fetal heart rate of 140 bpm, moderate variability, and three accelerations (15 bpm × 15 seconds) in 20 minutes. How should the nurse interpret this?

  1. AOption (a)

    Positive NST – indicates fetal distress

  2. BOption (b)

    Non-reactive NST – further testing needed

  3. COption (c)

    Reactive NST – baby is doing well

  4. DOption (d)

    Sinusoidal pattern – suggests severe fetal anemia

View answer & explanation

Correct answer

Answer: (c)C.

Reactive NST – baby is doing well

Why this answer is correct

Correct Answer: Reactive NST – baby is doing well

Rationale:

  • A Non-Stress Test (NST) is used to evaluate fetal well-being by assessing fetal heart rate patterns in response to fetal movement. A healthy fetus should demonstrate accelerations that reflect adequate oxygenation and neurological function.
  • A “reactive” NST is defined as two or more accelerations of at least 15 beats per minute above baseline lasting for at least 15 seconds within a 20-minute window for pregnancies ≥32 weeks.
  • In this case, the NST shows a baseline fetal heart rate of 140 bpm (normal), moderate variability (good indicator of fetal oxygenation), and three accelerations that meet the 15×15 criteria.
  • The presence of adequate accelerations and normal variability confirms that the fetus is well-oxygenated and neurologically responsive, which defines a reactive NST.
  • A reactive NST indicates the baby is doing well, and no further immediate testing is required unless other clinical concerns are present.

Explanation of Other Options:

Non-reactive NST – further testing needed

  • Rationale: A non-reactive NST lacks the required accelerations. This patient has three accelerations meeting criteria, so the NST is reactive, not non-reactive.

Positive NST – indicates fetal distress

  • Rationale: “Positive” is a term used for the Contraction Stress Test (CST), not NST. NST results are interpreted as reactive or non-reactive.

Sinusoidal pattern – suggests severe fetal anemia

  • Rationale: A sinusoidal pattern is smooth, wavelike, and absent of variability or accelerations. This fetus has normal variability and accelerations, so this pattern is not present.

Conclusion:

  • With moderate variability, a normal baseline, and three accelerations meeting the 15×15 rule, the NST is clearly reactive, indicating the baby is healthy and well-oxygenated.

Question 20

AIIMS Nursing Officer 2025• Section 1

Anaphylactic shock is a severe allergic reaction that causes widespread vasodilation and fluid leakage from blood vessels. This type of shock is classified as:

  1. AOption (a)

    Cardiogenic shock

  2. BOption (b)

    Distributive shock

  3. COption (c)

    Hypovolemic shock

  4. DOption (d)

    Obstructive shock

View answer & explanation

Correct answer

Answer: (b)B.

Distributive shock

Why this answer is correct

Correct Answer: Distributive shock

Rationale:

  • Anaphylactic shock is a life-threatening form of severe allergic reaction caused by massive release of chemical mediators such as histamine, leukotrienes, and prostaglandins from mast cells and basophils.
  • These mediators result in profound vasodilation and increased capillary permeability, causing fluid to leak out of blood vessels into the tissues, leading to relative hypovolemia and severe hypotension.
  • Because the primary problem in anaphylaxis is maldistribution of blood flow rather than actual blood loss or pump failure, it is classified under distributive shock.
  • Distributive shock includes three main types: septic shock, neurogenic shock, and anaphylactic shock, all characterized by widespread vasodilation and altered vascular tone.
  • Therefore, based on its pathophysiology—massive vasodilation and fluid shift—anaphylactic shock is correctly categorized as distributive shock.

Explanation of Other Options:

Cardiogenic shock

  • Rationale: Cardiogenic shock occurs due to pump failure (e.g., myocardial infarction). Anaphylaxis does not involve heart pump failure as the primary issue.

Hypovolemic shock

  • Rationale: Hypovolemic shock results from actual loss of blood or fluids (e.g., hemorrhage, dehydration). In anaphylaxis, the volume loss is relative, due to vasodilation, not true loss.

Obstructive shock

  • Rationale: Obstructive shock occurs when blood flow is physically blocked (e.g., pulmonary embolism, cardiac tamponade). This mechanism does not apply to anaphylaxis.

Conclusion:

  • Anaphylactic shock involves widespread vasodilation and increased capillary permeability, making it a classic example of distributive shock.